



It depends which treatment you mean, and the difference is the whole answer. Spravato, the prescription nasal spray, is FDA-approved for treatment-resistant...
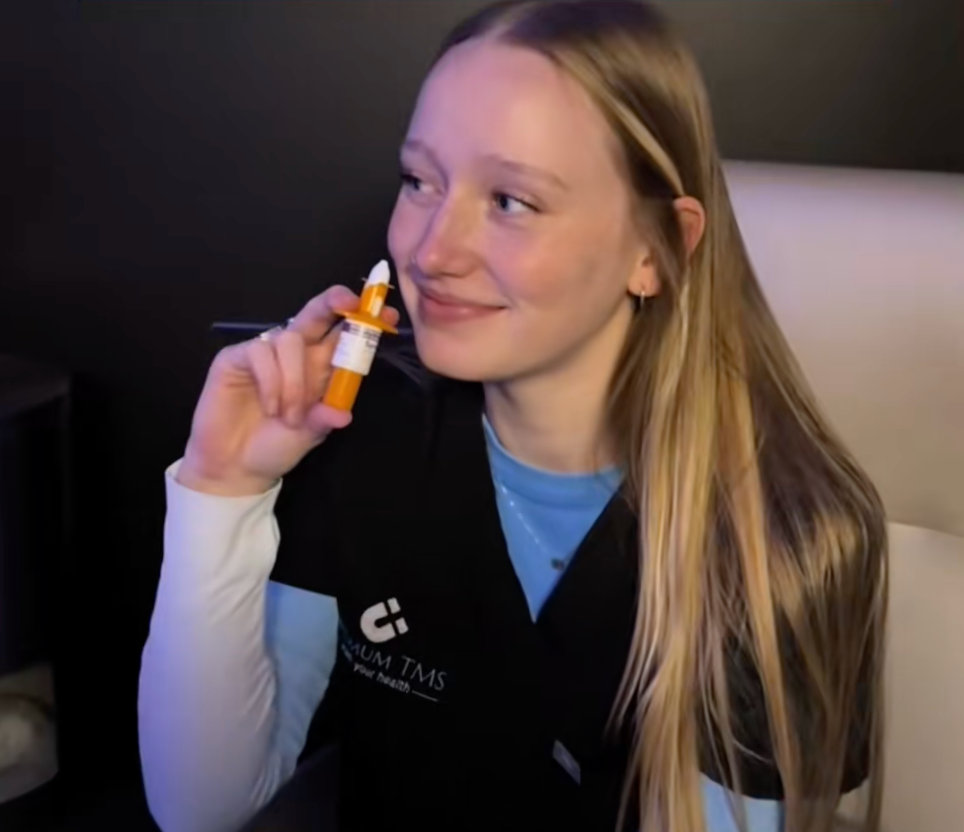
Most Spravato side effects happen during the monitoring period at the clinic and settle before you go home. The day after is usually unremarkable for most pe...

IV ketamine at Optimum TMS is $450 a session or $2,400 for six, cash-pay only. Why insurance doesn't cover it, and which alternatives usually are.

When antidepressant refills aren't enough. Focused psychiatric medication management in Columbus for depression and OCD, with measured follow-up.
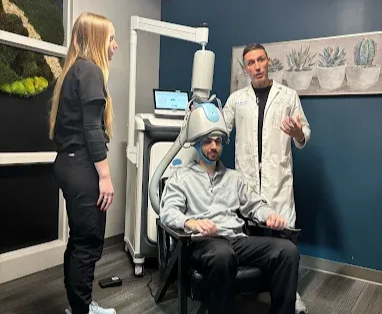
Quick Answer: For many people, improvement holds after the final session, and some continue improving for weeks afterward. Others find symptoms return months or years later. That isn't a sign the treatment failed. What protects your result is staying on whatever your prescriber recommends, keeping the routines that got built during treatment, and staying connected to a provider so a dip gets caught early rather than after it's taken hold. If symptoms do come back, retreatment is an option and many people respond again. Session 36 is a strange appointment. You've been coming in five days a week for weeks, and then it stops. Most of the information available about TMS covers everything up to that point and almost nothing after it. This post covers what to expect once the course ends, what makes results more likely to hold, what a relapse actually looks like, and what your options are if one happens. The first few weeks after your last session Two things surprise people. Improvement can keep going. Some people notice further gains in the weeks after treatment finishes. If you ended the course feeling better but not finished, that isn't necessarily where you'll stay. The structure disappears. For six or seven weeks you had a daily appointment, a reason to be somewhere, and regular contact with clinicians who asked how you were. That scaffolding was doing more than delivering the treatment, and losing it is a real adjustment. People sometimes read the flatness of that first week off as symptoms returning when it's the loss of routine. If you can, put something in the slot the appointments used to occupy. It doesn't have to be therapeutic. It has to be regular. What makes results more likely to hold There's no way to guarantee a durable result, but a few things are worth getting right. Stay on your medication unless your prescriber says otherwise . This is the most common mistake. Feeling better after TMS makes stopping antidepressants tempting, and doing it unilaterally is a well-worn route back to where you started. If you want off them, that's a legitimate conversation to have with your prescriber, who can taper you properly. Keep a prescriber. If you don't have one, that's worth sorting out before you need one rather than during a dip. Consider therapy if you aren't already doing it . TMS can lift symptoms far enough that therapy becomes possible in a way it wasn't when you were at your worst. The window right after treatment is often the best time to start. Protect sleep, movement, and alcohol intake. Unglamorous, and they matter. Keep an eye on the measures. If you tracked symptom scores during treatment, keep doing it occasionally. A number moving in the wrong direction is easier to spot than a mood shifting slowly. What relapse actually looks like It's rarely a sudden collapse. It usually creeps: sleep goes first, or motivation, or the sense that everything requires more effort than it did a month ago. Because it's gradual, people often normalize it for a long stretch before recognizing what's happening. Signs worth acting on: Sleep or appetite shifting back toward how they were before treatment Withdrawing from people, cancelling things you'd normally do Concentration slipping The return of a specific symptom that was distinctive for you Someone close to you saying they've noticed a change That last one is worth taking seriously even when you disagree with it. Others often see it first. Set a threshold in advance. Decide now what would prompt you to call: two weeks of worsening sleep, say, or a rating scale score crossing a specific point. Making that decision while you're well is far easier than making it while you're unwell. If thoughts of harming yourself return at any point, call or text 988 or go to your nearest emergency department. Don't wait for an appointment.

Quick Answer: The questions that matter most are who prescribes and oversees your treatment, whether the clinic verifies your insurance before you start , how they measure whether it's working, and what they do if it isn't. The daily commute matters more than people expect, because a standard course means five appointments a week for roughly six weeks. Most of the things clinics advertise on are less useful for choosing than these. If you've searched "TMS near me" in Columbus, you've probably found several options and no real basis for picking between them. Every website says the same things: FDA-cleared, non-invasive, covered by insurance. All true, all unhelpful for making a decision. These are the questions that actually separate one clinic from another. Ask them of us, and ask them of everyone else you're considering. 1. Who prescribes and oversees the treatment? TMS is a medical treatment, and who is responsible for it varies more between clinics than you'd expect. Some are psychiatrist-led. Some have TMS prescribed by providers from other specialties. This matters clinically , because depression that hasn't responded to medication sometimes turns out to be something other than straightforward depression, and spotting that requires psychiatric assessment rather than a TMS referral. It can also matter administratively, since insurance criteria include requirements about evaluation and oversight. Ask directly: who evaluates me, who prescribes, and are they a psychiatrist? If you've been turned down for TMS elsewhere, ask whether the reason was clinical or a documentation issue, because those have different fixes. There's more on this in our post on whether you need a psychiatrist, a therapist, or both . At Optimum, treatment is overseen by Dr. Mark E. Blair, MD, a board-certified psychiatrist and our Medical Director. 2. What device do they use, and is it cleared for your condition? Not all TMS systems are the same, and FDA clearance is condition-specific. A device cleared for depression is not automatically cleared for OCD or for adolescents. If you're seeking treatment for depression, most systems will be appropriate. If you're asking about OCD, or about TMS for a teenager, this question narrows the field considerably. Optimum uses BrainsWay Deep TMS, which uses a helmet-based coil rather than a figure-8 coil, and is FDA-cleared for depression, for OCD, and for adolescents aged 15 and over. 3. What happens if TMS doesn't work for me? Ask this one before you start, not at session 30. TMS helps a lot of people and doesn't help everyone. What you want to know is whether the clinic has somewhere to go from there, or whether TMS is the only thing they do. A clinic that also offers Spravato , IV ketamine , and psychiatric medication management can adjust course without you starting over somewhere new. Be wary of anyone who won't engage with the question. A provider who is comfortable telling you that some people don't respond is giving you a more honest picture than one who isn't. 4. Will they verify your insurance before you start? This is the question that saves people the most money and the most stress. TMS is FDA-cleared for depression and covered by most major insurance plans when criteria are met, but "covered" means different things depending on your deductible, your coinsurance, and where you are in your plan year. You should know your expected out-of-pocket cost before your first session, in writing if possible. Ask specifically: Do you verify benefits before treatment starts? Are you in network with my plan? What's my expected out-of-pocket cost for a full course? What happens if my plan denies the authorization? Is anything you're recommending self-pay rather than insurance-billable? That last one matters. Accelerated protocols, for instance, are typically self-pay rather than insurance-billable, and you want that clear upfront rather than discovered later. 5. How will you know if it's working? The weak answer is "we'll ask how you're feeling." Depression is a poor judge of its own severity, and asking someone in week three whether they feel better produces unreliable information. The better answer involves standardized symptom rating scales used at intervals throughout the course, so improvement is tracked rather than recalled. Ask what they use, how often, and whether you'll see the results. Ask what happens if the numbers aren't moving by the midpoint. There should be an answer.
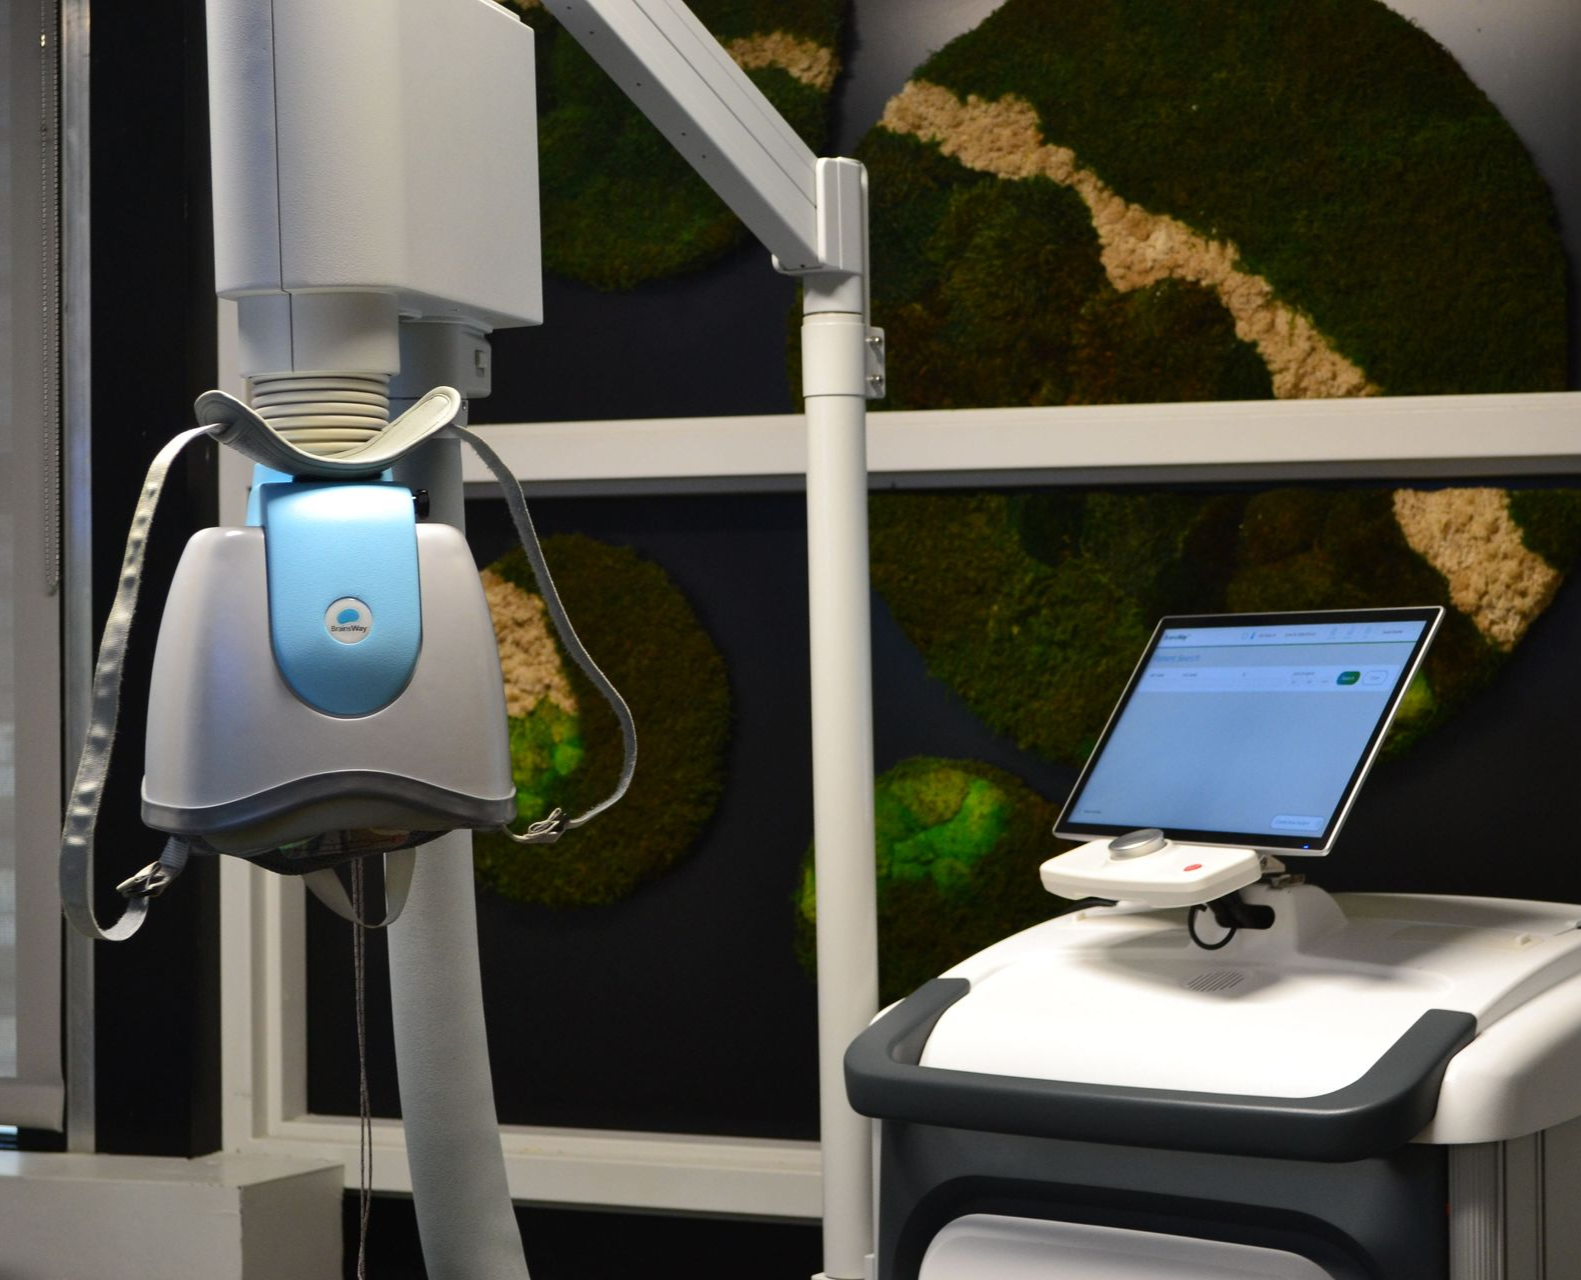
Quick Answer: A standard course of TMS at Optimum is 36 session s, done on weekdays over roughly six to seven weeks. Each session is up to 20 minutes in the chair, and you're awake the whole time, with no sedation and no recovery period. You drive yourself there and drive yourself home. The most common side effect is scalp discomfort or a headache during the first week, which usually settles as you adjust. The biggest thing to plan for isn't the treatment itself. It's the daily commute. Most people researching TMS have already read that it's non-invasive and FDA-cleared. What they can't find is what it's actually like to do - what the first session feels like, whether you can work, when people start noticing anything. This is that account, in order. Before you start Two things happen first. The consultation. A psychiatric evaluation to confirm TMS is appropriate for you, go through your medication history, and check for anything that would rule it out. This is also where benefits get verified, so you know your cost before you commit rather than after. The mapping session. Your first appointment in the chair is longer than the rest. The clinician locates the treatment area on your head and determines your motor threshold — the stimulation level right for you specifically. You'll usually see your thumb or fingers twitch during this part. It's odd to watch and completely normal. Those coordinates are recorded so every subsequent session targets the same spot. Bring your treatment history to the consultation if you have it. It's the thing that most often holds up an insurance approval. Week 1: getting used to it What a session is like. You sit in a chair, upright, in your own clothes. The coil is positioned against your head. When the pulses start you'll hear a rapid clicking sound and feel a tapping sensation on your scalp. You wear earplugs. You're fully awake and can talk to the technician throughout. The pulses come in short bursts with pauses between them. Up to 20 minutes in the chair, then you stand up and leave. What it feels like. People describe the tapping as anything from a woodpecker to a rubber band flick. The first few sessions are the most uncomfortable, partly because it's unfamiliar and partly because the sensation genuinely takes some adjusting to. If it's too much, say so — the intensity can be adjusted while you get used to it. Side effects this week. Scalp discomfort at the treatment site and headaches are the most common , and they're usually mild and manageable with over-the-counter pain relief. Both typically ease over the first week or two. Some people notice tiredness or lightheadedness immediately afterward. What you can do afterward. Everything. There's no sedation, no observation period, and no restriction on driving. People routinely go straight back to work. Weeks 2 to 3: it becomes routine By the second week, most people have stopped thinking about the sessions as an event. The scalp sensation usually feels much less noticeable - not because the intensity dropped, but because you've adjusted to it. This is where the real demand of TMS becomes clear, and it isn't clinical. It's five appointments a week. People read books, listen to podcasts, take calls beforehand. What actually determines whether the course goes smoothly is whether the appointment slot fits your day, so pick that carefully at the start rather than trying to move it later. Don't expect much yet . Some people notice changes early. Many don't, and that isn't a bad sign. This is the stretch where people most often get discouraged, usually because they've read someone else's account of feeling better in week two. Weeks 4 to 6: where change tends to show up If TMS is going to work for you, this is generally the window where it becomes noticeable - though it varies, and some people respond later in the course. It rarely arrives as a dramatic lift. What people describe more often is a series of small, specific things: sleeping better, getting through the day without the afternoon collapse, replying to a message they'd have left for a week, noticing they laughed at something. Family and colleagues often see it before the patient does. Progress is measured, not guessed at. Symptom rating scales are used throughout the course so the picture doesn't depend on how you happen to feel on the day you're asked. If nothing has changed by now, raise it. That's a real conversation to have with your provider about whether anything should be adjusted, not something to sit on until the end.
Quick Answer: Spravato is FDA-approved for treatment-resistant depression and is typically covered by most major insurance plans, including Medicare and Medicaid, when criteria are met. Coverage isn't only for the consultation. It generally applies to the ongoing treatment itself, though there are usually two separate charges - the medication and the in-clinic monitoring - and your out-of-pocket cost depends on your specific plan. Optimum verifies your benefits before you start. One fear comes up more than any other with this treatment: that insurance covers the consultation, you get told you're a good candidate, and then the real cost lands after you're already invested. It's a reasonable thing to worry about, because it does happen with some medical treatments and because nobody explains the billing until you ask. Here's how Spravato is actually billed , what's usually covered, and the questions to ask before you commit to anything. Does insurance cover Spravato, or just the consultation? The treatment, not just the consultation. Spravato (esketamine) is FDA-approved for treatment-resistant depression , and that approval is why it sits in a different category from off-label treatments. Most major insurance plans cover it when the medical criteria are met, and Optimum accepts most private and public plans including Medicare and Medicaid. What varies is not usually whether it's covered but how much you pay — your deductible, copay or coinsurance, and whether you've met your out-of-pocket maximum for the year. Two people with the same diagnosis at the same clinic can pay very different amounts because their plans are different. The consultation-only fear is worth naming because it usually comes from a real experience with a different treatment, often something off-label. IV ketamine is the clearest example: it's used off-label for depression rather than under a depression-specific FDA approval, and it's self-pay . Spravato is a different situation entirely, and it's worth not letting one experience set your expectations for the other. Why there are usually two charges, not one This is the part that catches people out, and it isn't a hidden fee. It's how the treatment is structured. The medication. Spravato is a prescription nasal spray, and it's billed as a drug. The in-clinic monitoring. You self-administer the spray at a certified treatment center under supervision, then stay for an observation period before going home. That clinical time is billed separately from the medication. Both are typically covered when Spravato is covered, but they can appear as separate line items and may be processed differently by your plan. If you're calling your insurer yourself, ask about both. Asking only about the drug can give you an incomplete answer. You'll also need a ride home after each session, which isn't a billing item but is a real cost to plan for if you're arranging transport. What insurers usually want to see Coverage for Spravato generally depends on meeting criteria for treatment-resistant depression. In practice, that usually means documented antidepressant trials that didn't produce an adequate response, and the assessment looks at whether each trial was at a therapeutic dose for a sufficient duration. This is why your medication history matters so much. People are sometimes told they don't meet criteria when the underlying problem is that years of treatment were never documented properly. If you have a record of what you took, at what dose, for how long, bring it. If you don't, our post on what counts as an adequate medication trial explains what to reconstruct. Spravato is also prescribed alongside an oral antidepressant rather than instead of one, which is part of how it's approved and how it's assessed for coverage.
Quick Answer: Longer than most people do, but not indefinitely. Antidepressants need several weeks at a therapeutic dose before you can fairly judge whether they're working, and side effects usually show up before benefits do. Your prescriber will have a specific review point in mind. What matters is that the trial is long enough, at a high enough dose, taken consistently, because those three things are what make it count as a real trial rather than an inconclusive one. Most people either stop too early or wait far too long. Stopping at two weeks because nothing has changed means you never find out whether the medication would have worked. Staying on something for two years because it's "probably doing something" costs you the same time in a different way. This post covers what should happen in the early weeks, what makes a trial count, and why keeping a record of it matters more than you'd expect. Why it takes weeks rather than days Antidepressants change neurotransmitter levels fairly quickly, but the downstream changes that actually shift mood take longer to develop. That gap is why the first stretch on a new medication can feel like the worst of both worlds: you're getting the side effects without any of the benefit. This isn't the medication failing. It's the normal shape of the thing. Knowing that in advance is the single best predictor of whether someone sticks with a trial long enough to learn anything from it. Improvement is also usually gradual rather than sudden. People often notice it first in sleep, appetite, or energy, and only later in mood. Sometimes the people around you notice before you do. What should happen in the first few weeks? Expect side effects early. Nausea, headaches, restlessness, changes to sleep, and digestive upset are common at the start and often ease as your body adjusts . Your prescriber can tell you which ones are expected to settle and which ones aren't. When to call sooner rather than waiting it out: Your mood gets noticeably worse rather than better New or increasing agitation, restlessness, or inability to sit still New or worsening thoughts of harming yourself Any side effect that's severe, or that you can't function around A rash, or anything that feels like a physical reaction rather than an adjustment None of these are reasons to be stoic. Early worsening is uncommon but it's real, and it's specifically why prescribers want to see you sooner after a start or a dose change rather than later. If you're having thoughts of harming yourself, call or text 988, or go to your nearest emergency department. Don't wait for your next appointment. Don't stop a medication abruptly on your own either. Several antidepressants cause discontinuation symptoms if stopped suddenly, and those get mistaken for relapse. If you want off it, tell your prescriber that and they'll taper you. What actually counts as an adequate trial Three things have to be true before a medication trial tells you anything useful: A therapeutic dose. Many people are titrated up gradually and then stay at a starting dose that was never meant to be the destination. A trial at the lowest dose isn't a failed trial. It's an incomplete one. Enough time at that dose. The clock starts when you reach the therapeutic dose, not when you first took the tablet. This is where a lot of "failed" trials fall apart on review. Consistent use. Missed doses, stopping and restarting, or gaps caused by cost or pharmacy issues all muddy the result. Say so honestly at your review appointment. Prescribers are not shocked by this, and it changes what they recommend. If any of the three is missing, the honest answer is that you don't yet know whether the medication works for you.

Quick Answer: They do different jobs. A therapist treats symptoms through structured talk therapy. A psychiatrist or psychiatric nurse practitioner diagnoses, prescribes medication, and oversees medical treatments like TMS and Spravato. For moderate to severe depression and for OCD, most people do best with both. Which one you start with depends on your symptoms and what you've already tried. The question usually comes up at a practical moment: you've decided to get help and you're looking at two categories of provider with overlapping titles, or you've been seeing one of them for a while and you're not getting better. The distinction matters more than it looks, particularly if you're heading toward treatments that require a specific kind of prescriber. Here's who does what, when you need both, and where our own program fits. What a therapist does Therapists deliver structured psychotherapy. Depending on their training, that might be cognitive behavioral therapy (CBT), exposure and response prevention (ERP) for OCD, or trauma-focused approaches like EMDR or prolonged exposure. Sessions are usually weekly and run about an hour. Therapists in Ohio don't prescribe medication. That's the clean dividing line. What therapy is good at: changing the patterns that keep symptoms running, processing trauma, and building skills you keep after treatment ends. For OCD in particular, ERP isn't a nice-to-have alongside medication. It's a first-line treatment in its own right. What a psychiatrist does A psychiatrist is a medical doctor (MD or DO) who completed medical school, a psychiatric residency, and in many cases board certification. They diagnose, prescribe and manage medication, and oversee medical treatments including TMS and Spravato . Some psychiatrists also provide therapy, though many focus on medication and interventional treatment and work alongside therapists. A psychiatric nurse practitioner (PMHNP) is an advanced practice registered nurse with specialist psychiatric training who can evaluate, diagnose, and prescribe. In practice, a PMHNP working within a psychiatrist-led practice covers much of the same ground for straightforward medication management, with the medical director available for more complex cases. That's the model here: Dr. Mark Blair, MD , board-certified psychiatrist and Medical Director, with a psychiatric nurse practitioner providing medication management. When you need both For moderate to severe depression, combining medication with therapy generally works better than either on its own. They're doing different things. Medication addresses the biology; therapy addresses what you do with your days, your thinking, and your relationships. Neither substitutes for the other. For OCD, the standard combination is an SSRI plus ERP therapy. Medication alone tends to take the edge off without teaching you how to stop the compulsions. For PTSD, trauma-focused psychotherapy does the primary work, with medication supporting sleep, mood, and anxiety while you do it. If you're only seeing one and you've plateaued, adding the other is often the change that moves things, not another dose adjustment. Does it matter who prescribes? For a first antidepressant, often not much. Primary care physicians prescribe antidepressants routinely and are a perfectly reasonable place to start. It starts to matter in three situations: When treatment isn't working. Several failed medication trials is the point where diagnostic review by a psychiatric specialist adds something a routine refill appointment can't. When the diagnosis may be incomplete. Bipolar spectrum illness, OCD, and PTSD respond to different treatment than unipolar depression, and mistaking one for the other costs years. When you're moving toward interventional treatment. This is where credentials become a practical hurdle rather than a preference. TMS and Spravato both sit inside specific clinical and regulatory frameworks. Spravato can only be given at a certified treatment center under supervision, which is not something any prescriber can arrange. TMS is FDA-cleared for depression and covered by most major insurance plans when criteria are met , but those criteria include requirements around evaluation and oversight, and plans vary in how they define them. The practical consequence: if you've been told you don't qualify for TMS, it's worth finding out whether the reason was clinical or administrative. Those have very different fixes. A clinical exclusion means the treatment genuinely isn't appropriate for you. A documentation or credentialing issue means the treatment might be appropriate and the paperwork didn't support it. Ask which one it was, and bring that answer to your next consultation. At Optimum, TMS and Spravato are prescribed and overseen by a board-certified psychiatrist, and benefits are verified before you commit to anything .











